Why Migraine Nausea Arrives Before the Head Pain
Quick Answer: Migraine nausea often precedes head pain because the same brainstem structures that initiate an attack also regulate the vomiting reflex and stomach motility, so gastrointestinal symptoms can appear during the prodrome hours before pain begins. Stomach emptying slows during this phase, which is why oral medication taken after pain starts often works poorly. Treating at the first nausea rather than the first pain is the single most practical implication, and it is worth discussing formulation options with a clinician if oral tablets consistently fail you.
Most people describe migraine as a headache with nausea attached. A large share of people who actually get them describe it the other way round.
The stomach turns first, sometimes hours before anything hurts. Food stops appealing. And by the time the pain arrives, the tablet you swallowed is sitting in a stomach that has essentially stopped working.


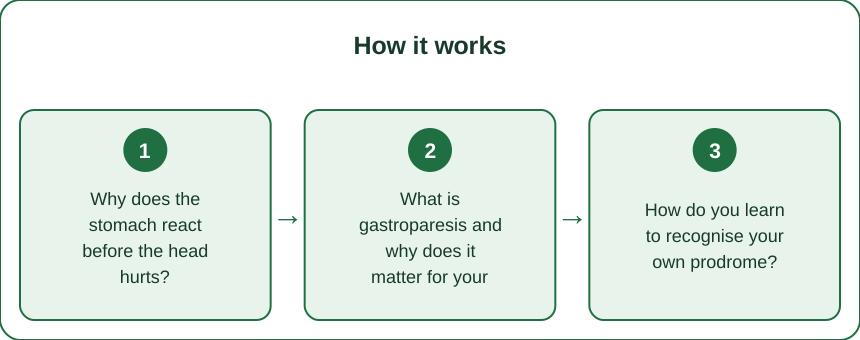
Why does the stomach react before the head hurts?
Because an attack starts well before the pain phase, and it starts in a part of the brain that also runs your gut.
The prodrome is a real, measurable phase. It begins anywhere from two to 48 hours before pain and includes yawning, food cravings, mood change, neck stiffness, frequent urination, light sensitivity, fatigue, and nausea. Brain imaging studies during spontaneous attacks show hypothalamic activation during this phase, before any pain.
The anatomy explains the overlap. Several structures involved in migraine initiation sit alongside or connect directly to the structures controlling nausea and vomiting:
- The hypothalamus, active early in an attack, has extensive connections to autonomic control centres including those regulating gut function.
- The area postrema, in the brainstem, is the chemoreceptor trigger zone for vomiting. It sits next to structures involved in trigeminal pain processing.
- The nucleus tractus solitarius receives vagal input from the gut and connects to both.
The neurochemistry overlaps too. Serotonin and dopamine are involved in both migraine mechanisms and nausea signalling, and calcitonin gene-related peptide, the target of newer migraine drugs, affects gut motility as well.
What this means practically: the nausea is not a reaction to the pain. It is a parallel symptom of the same underlying process, and it frequently arrives first because the systems involved respond at different speeds.
What is gastroparesis and why does it matter for your medication?
It is delayed stomach emptying, and during a migraine it is the reason oral tablets fail.
What happens. Gastric motility slows markedly during a migraine attack, and studies using various measurement methods have found significantly delayed emptying during attacks compared with pain-free periods. In some measurements, emptying is delayed even between attacks in people with frequent migraine.
Why it matters for treatment. An oral tablet has to reach the small intestine to be absorbed. If the stomach is not emptying, the tablet sits there. This produces a specific, recognisable pattern:
- You take the medication and nothing happens for an hour or more
- Then it either works suddenly and late, when the stomach finally empties, or not at all
- Sometimes you vomit and the tablet comes back up intact
The timing implication is the whole point of knowing this. Taking medication during the prodrome, before or at the very start of the nausea, means it is absorbed while the stomach still works. Waiting for pain often means waiting until absorption is compromised.
Options when oral absorption is unreliable, all of which are conversations to have with a clinician rather than decisions to make alone:
- Non-oral formulations, including nasal sprays, injectables, and dissolving films that bypass the stomach
- Adding an antiemetic that also promotes gastric motility, a common combination approach
- Effervescent or soluble formulations, which are absorbed somewhat faster than solid tablets
What not to do: repeatedly redosing an oral medication because the first dose seemed not to work. If the issue is absorption rather than efficacy, you may absorb everything at once when the stomach eventually empties. Dose limits exist for a reason.

How do you learn to recognise your own prodrome?
By tracking symptoms rather than triggers, which is a different exercise from the one most people are told to do.
The problem with trigger diaries. People are usually told to log what they ate and did before an attack. Because the prodrome includes food cravings and changes in activity, prodrome symptoms get logged as triggers. This is why chocolate has such a persistent reputation and such weak evidence: for some people, craving chocolate is a prodrome symptom, so the craving precedes the attack and gets blamed for it.
Track these instead, for four to six weeks, at a fixed time each evening:
- Yawning, particularly repetitive yawning that seems disproportionate to tiredness. One of the most specific prodrome signs.
- Neck stiffness or discomfort, reported by a large share of people and frequently mistaken for a cause.
- Nausea or loss of appetite, including food simply seeming unappealing.
- Mood change, irritability or unusual flatness.
- Urinary frequency and thirst.
- Light or sound sensitivity before any pain.
- Difficulty finding words or a general sense of mental fog.
What you are looking for is your personal pattern. Most people have two or three reliable prodrome symptoms that recur, and identifying them buys you a treatment window of hours.
A realistic expectation. Prodrome recognition is imperfect. You will treat some attacks that were not coming and miss some that were. Discuss with your clinician what an acceptable frequency of early treatment looks like given your medication and dose limits, because medication overuse headache is a genuine risk with frequent treatment.
What Nobody Tells You About Migraine Nausea
Abdominal migraine is a recognised diagnosis. In some people, particularly children, attacks present as abdominal pain and nausea with little or no head pain. Many of them go on to develop typical migraine as adults. If your child has recurrent unexplained stomach pain with a family history of migraine, this is worth raising specifically.
Nausea predicts treatment response. Research has found that people with prominent nausea have poorer response to oral triptans, which is consistent with the absorption explanation and is a reason to mention the nausea explicitly to your clinician rather than only the pain.
Motion sensitivity often runs alongside. Many people with migraine report car sickness in childhood and ongoing sensitivity to visual motion. The vestibular system connects to the same brainstem structures, and vestibular migraine is a distinct and underdiagnosed presentation.
The nausea can outlast the pain. The postdrome, or migraine hangover, includes fatigue, difficulty concentrating, and often lingering queasiness for up to 24 hours after the pain resolves. This phase is real and gets almost no attention.
Eating during the prodrome is complicated. Appetite drops, and skipping meals is itself a well-documented trigger for the next attack. Something small and bland during the prodrome is generally better than nothing, even when nothing appeals.
Ginger has modest evidence. Small trials have compared ginger with standard antiemetics for migraine-associated nausea with reasonable results. It is not a substitute for prescribed treatment and it is a low-risk addition for many people.
Dehydration compounds it in both directions. Nausea reduces fluid intake, dehydration worsens migraine, and vomiting accelerates both. Small, frequent sips are more tolerable than trying to drink a glass.
Seasonal note: the shift into autumn brings barometric pressure swings, which are one of the more consistently reported environmental triggers, and shorter days shift sleep timing. Both raise attack frequency for many people over the next several weeks, which makes this a good moment to have the treatment-timing conversation before you need it.
This is general information, not medical advice. Sudden severe headache unlike your usual pattern, headache with fever or neck rigidity, headache after head injury, or new neurological symptoms need urgent medical assessment.
FAQ: Migraine Nausea Questions, Answered
Why do I feel sick before my migraine starts?
The prodrome phase begins hours before pain, driven by hypothalamic and brainstem activity. Those same structures regulate nausea and gut motility, so the stomach symptoms can appear well before the head pain.
Why does my migraine tablet not seem to work?
Stomach emptying slows during attacks, so oral medication is poorly absorbed once symptoms are established. Taking it at the first sign rather than at the first pain often makes a substantial difference. Discuss non-oral formulations with your clinician if this is a recurring pattern.
Can you have migraine nausea without a headache?
Yes. Abdominal migraine presents with nausea and abdominal pain and little or no head pain, and it is more commonly diagnosed in children. Vestibular migraine can also present with dizziness and nausea without prominent headache.
TL;DR:
- Nausea is a parallel symptom of the same brain process that produces migraine pain, not a reaction to it.
- Stomach emptying slows during attacks, which is why oral medication taken late often works poorly or not at all.
- Treating at the first prodrome sign rather than the first pain is the practical implication worth discussing with your clinician.
- Track prodrome symptoms rather than triggers for six weeks. Cravings logged as triggers are frequently prodrome signs.
Start a simple evening log of yawning, neck stiffness, and appetite this week. Most people find a pattern within a month.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
